
Mastocytosis:
Posted: 19th September 2026 | Posted by: AdminMR
Mast cell disorders: patient and clinician guide
Mastocytosis: symptoms, diagnosis, types and treatment
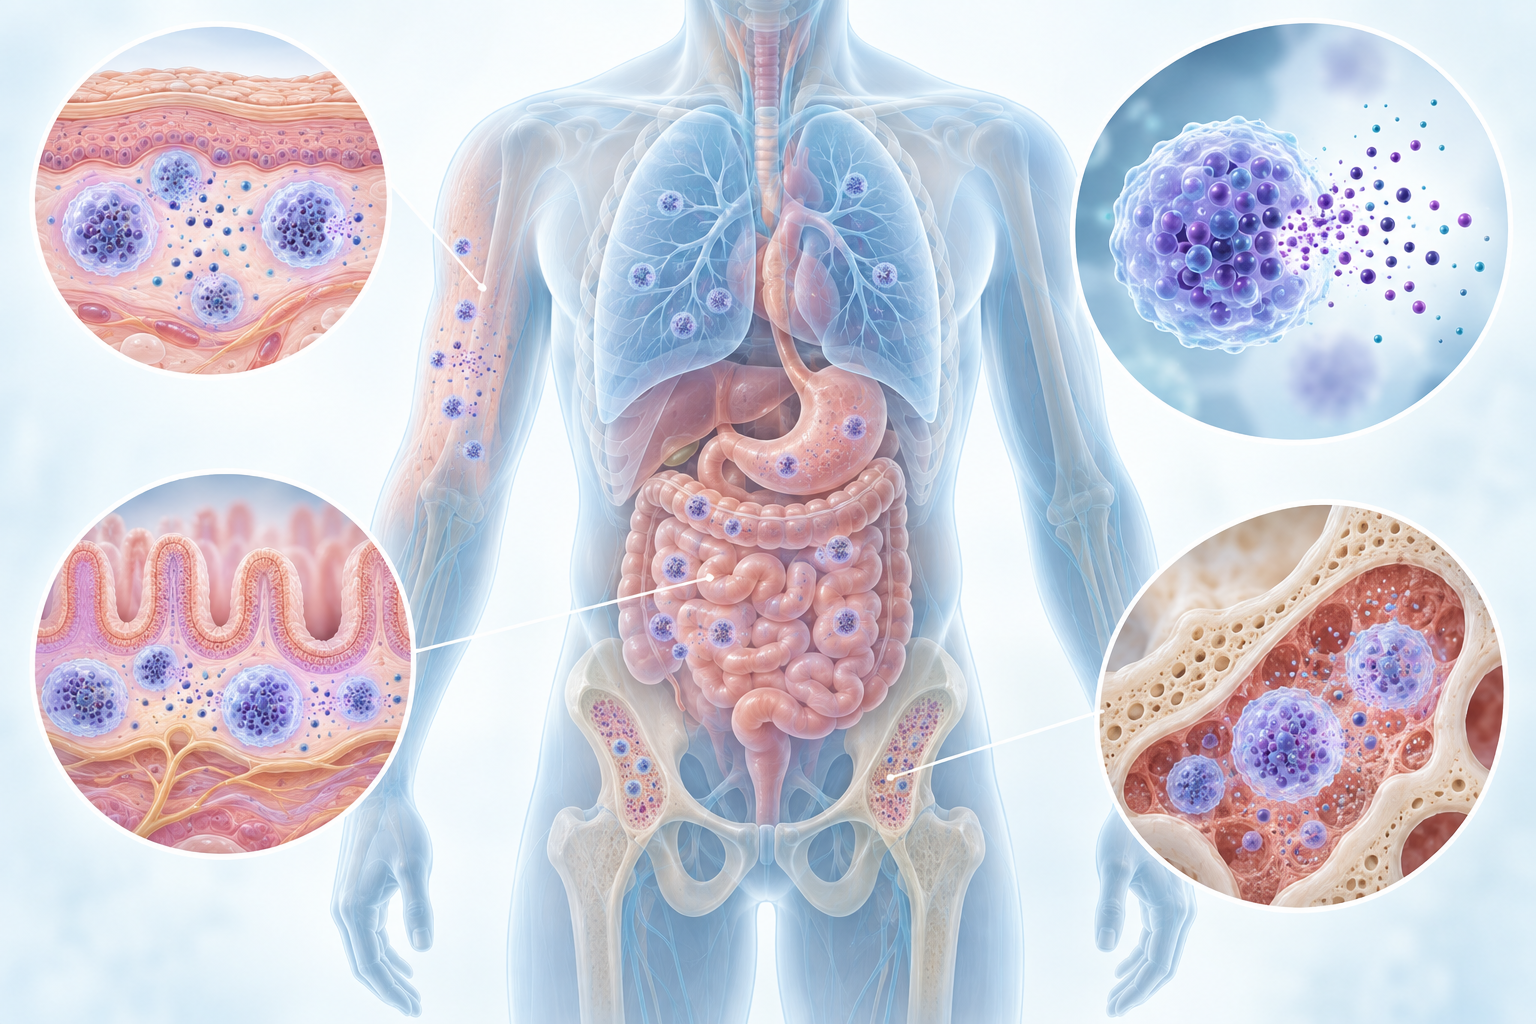
Mastocytosis is a rare group of disorders in which abnormal mast cells accumulate in the skin, bone marrow or other organs. This guide explains the recognised forms of mastocytosis, diagnostic tests, anaphylaxis and bone-health risks, established treatment, and important emerging research.
On this page
What mastocytosis is ·
Types ·
Symptoms ·
Anaphylaxis ·
Diagnosis ·
Tryptase and HαT ·
Bone health ·
Treatment ·
Emerging research ·
Children ·
References
What is mastocytosis?
Mast cells are immune cells that help protect the body and take part in allergic and inflammatory responses. They contain mediators such as histamine, tryptase, prostaglandins and leukotrienes. In mastocytosis, a clonal population of abnormal mast cells accumulates in one or more tissues.
Symptoms can arise in two different ways. Release of mast-cell mediators can cause itching, flushing, abdominal symptoms, low blood pressure and anaphylaxis. In systemic disease, infiltration of organs by abnormal mast cells can also affect bone, bone marrow, liver, spleen or the gastrointestinal tract. The number of mast cells does not always match symptom severity: some people with a relatively low disease burden experience substantial symptoms.
Most adult systemic mastocytosis is driven by an acquired activating mutation in KIT, usually KIT D816V. This mutation is not generally inherited from a parent. Mastocytosis is distinct from mast cell activation syndrome (MCAS), although both can involve episodes of mast-cell mediator release.
Types of mastocytosis
Cutaneous mastocytosis
Abnormal mast cells are limited predominantly to the skin. It is most often recognised in childhood and can present with maculopapular lesions, itching, blistering or diffuse skin involvement. Rubbing a lesion may cause swelling and redness, known as Darier’s sign.
Indolent systemic mastocytosis and bone marrow mastocytosis
Clonal mast cells are present outside the skin, usually in bone marrow, but there is no mast-cell-related organ damage. Symptoms and impaired quality of life may still be substantial. Bone marrow mastocytosis is a low-burden form that usually has no typical skin lesions.
Smouldering systemic mastocytosis
This has a higher mast-cell burden than indolent disease, with specified indicators of disease burden, but without the organ damage that defines advanced systemic mastocytosis.
Advanced systemic mastocytosis
This group includes aggressive systemic mastocytosis, systemic mastocytosis with an associated haematological neoplasm (SM-AHN), and mast-cell leukaemia. Advanced forms can cause cytopenias, liver dysfunction, malabsorption, pathological fractures or other organ damage and require specialist haematology care.
Mast-cell sarcoma is a separate, exceptionally rare and aggressive mast-cell tumour. Classification should follow current World Health Organization or International Consensus Classification criteria and be established by specialists.
Symptoms of mastocytosis
The clinical picture varies widely. Common manifestations include:
- Skin: itching, flushing, red-brown lesions, swelling and heat sensitivity.
- Gastrointestinal: abdominal pain, diarrhoea, nausea, reflux, bloating or malabsorption.
- Cardiovascular: palpitations, dizziness, low blood pressure or fainting.
- Neurological and general: fatigue, headache, concentration difficulties and impaired quality of life.
- Musculoskeletal: bone pain, osteopenia, osteoporosis or fragility fractures.
- Advanced disease: enlarged liver or spleen, abnormal blood counts, weight loss, impaired liver function or other organ dysfunction.
Possible triggers include insect venom, alcohol, heat or abrupt temperature change, friction, physical stress and certain medicines. Triggers differ between people. Broad avoidance lists and restrictive diets should not be adopted automatically; management is safer and more sustainable when based on a reproducible individual history.
New dietary evidence: a small prospective study of 20 people found no association between daily dietary histamine, fried food or alcohol intake and day-to-day symptom severity. This preliminary finding does not prove that foods can never trigger symptoms, but it supports avoiding indiscriminate dietary restriction and identifying personal triggers instead.
Mastocytosis and anaphylaxis
Systemic mastocytosis and other clonal mast-cell disorders can increase the risk and severity of anaphylaxis. Hymenoptera venom—particularly bee and wasp stings—is an important trigger, but reactions may also be associated with food, medicines or no identifiable trigger. Severe reactions can occur without prominent hives or skin symptoms.
Emergency: breathing difficulty, throat swelling, collapse or suspected anaphylaxis requires immediate emergency treatment. Use an adrenaline auto-injector if prescribed and call emergency services. People at risk should have an individual emergency plan and be shown how and when to use their injectors.
Adults with severe, recurrent or unexplained anaphylaxis—especially after an insect sting—may need evaluation for a clonal mast-cell disorder. The REMA score can help specialists estimate this probability, but it does not replace highly sensitive KIT testing or bone-marrow assessment when these are indicated.
Emerging data reinforce that mast-cell clonality matters. In a retrospective cohort of 303 adults with food-induced anaphylaxis, clonality was independently associated with severe reactions. HαT alone was not a marker of greater food-anaphylaxis severity in that cohort. These preliminary findings require peer-reviewed confirmation and should not be used alone to make individual risk decisions.
How is mastocytosis diagnosed?
Diagnosis combines symptoms and examination with laboratory, pathological, immunophenotypic and molecular findings. No single blood test can establish or exclude every form of mastocytosis.
Clinical assessment
Assessment includes skin lesions, anaphylaxis, gastrointestinal and skeletal symptoms, blood counts, medication and sting reactions, organ enlargement and evidence of organ dysfunction. A skin biopsy may support the diagnosis of cutaneous involvement.
Baseline and acute serum tryptase
A baseline serum tryptase level is useful when systemic mastocytosis is suspected. A persistent level above 20 ng/mL can fulfil one minor diagnostic criterion after relevant adjustments and exclusions, but a lower value does not rule out systemic disease. During suspected anaphylaxis, an acute tryptase sample should be compared with the person’s baseline; acute and baseline measurements answer different questions.
KIT mutation testing
KIT D816V can be present at a very low variant allele fraction in peripheral blood. A negative result from a low-sensitivity method does not reliably exclude systemic mastocytosis. Sensitive allele-specific PCR or digital PCR is preferable where available. Testing of bone marrow or another involved tissue may be necessary.
A recent laboratory study reported that an ultra-sensitive superRCA assay detected KIT D816V down to 0.0005% variant allele fraction in analytical samples. This is promising for low-burden disease and monitoring, but it remains an assay-development result rather than a replacement for validated clinical pathways.
Bone marrow and diagnostic criteria
In adults with suspected systemic mastocytosis, bone-marrow examination is often central. The major criterion is multifocal dense aggregates of mast cells in bone marrow or another extracutaneous organ. Minor criteria include atypical mast-cell morphology, an activating KIT mutation, aberrant expression of markers such as CD25, CD2 or CD30, and persistently raised baseline tryptase under defined conditions. Systemic mastocytosis is diagnosed when the major criterion plus at least one minor criterion, or at least three minor criteria, are fulfilled.
Important: WHO and ICC frameworks are similar but not identical. Diagnosis, subtype and treatment eligibility should therefore be confirmed by a multidisciplinary team experienced in mast-cell disease.
Serum tryptase and hereditary alpha-tryptasaemia
Hereditary alpha-tryptasaemia (HαT) is an inherited trait caused by increased germline copy number of alpha-tryptase-encoding TPSAB1. It commonly raises baseline serum tryptase and can coexist with mastocytosis, but it is not itself systemic mastocytosis.
HαT results may help interpret an elevated baseline tryptase. Current diagnostic frameworks allow adjustment of the tryptase criterion when HαT is present. Clinical expression is variable: some carriers are asymptomatic, while others report mediator-related or multisystem symptoms.
Recent research illustrates why cautious interpretation is necessary. Some selected referral cohorts associated HαT, greater alpha-tryptase copy number or coexisting HαT and systemic mastocytosis with higher tryptase or more severe reactions. Other cohorts found that HαT alone did not predict anaphylaxis frequency or severity, and a food-anaphylaxis study found clonality—not HαT—to be the strongest predictor. Collectively, the data support treating HαT as a context-dependent modifier, not a stand-alone explanation for every symptom or a universal measure of anaphylaxis risk.
Mastocytosis and bone health
Systemic mastocytosis can alter bone remodelling and cause osteopenia, osteoporosis, vertebral fractures, osteosclerosis or, less often, large osteolytic lesions. A fracture may occasionally be the feature that leads to diagnosis. Bone-health assessment may include fracture history, calcium and vitamin D status, bone density measurement and appropriate imaging.
Management can include adequate calcium and vitamin D where appropriate, weight-bearing activity, fall-risk reduction and osteoporosis treatment. Bisphosphonates, including intravenous zoledronate, may be used in selected patients under specialist supervision.
A retrospective study of 114 patients treated continuously with zoledronate for at least three years reported sustained improvement in bone density and suppression of bone turnover over a median 9.2 years. However, 47 incident fragility fractures—46 vertebral—still occurred, showing that improved bone-density results do not eliminate fracture risk. A separate exploratory Summit analysis reported increases in bone-formation markers after 24 weeks of bezuclastinib, but clinical fracture benefit has not yet been established.
Treatment of mastocytosis
Treatment depends on subtype, symptoms, anaphylaxis risk, organ involvement, mutation profile and patient priorities. It is useful to distinguish mediator-directed treatment from disease-modifying or cytoreductive treatment.
Control of mediator-related symptoms
- Non-sedating H1 antihistamines for itching, flushing and other histamine-mediated symptoms.
- H2 antihistamines or proton-pump inhibitors for selected upper gastrointestinal symptoms.
- Leukotriene-receptor antagonists or oral cromoglicate for selected patients.
- Omalizumab may be considered in specialist care for recurrent anaphylaxis or difficult mediator symptoms, although it does not eradicate the mast-cell clone.
- Individual trigger management without unnecessary restriction.
Anaphylaxis and venom allergy
Patients at risk require training and an emergency plan, including adrenaline auto-injectors when clinically indicated. Confirmed Hymenoptera venom allergy should be assessed for venom immunotherapy; patients with mastocytosis may require prolonged or lifelong treatment according to specialist risk assessment.
KIT-targeted treatment
Avapritinib is a selective inhibitor active against KIT D816V. The randomised PIONEER trial established improvement in symptoms and measures of mast-cell burden in adults with moderate-to-severe indolent systemic mastocytosis despite best supportive care. The AIMS observational study adds real-world evidence: among 98 patients with paired six-month data, quality of life, symptom scores, serum tryptase and blood KIT D816V variant allele fraction all improved. Because this was observational, it complements rather than replaces randomised evidence.
For advanced systemic mastocytosis, avapritinib and midostaurin are established targeted options in relevant jurisdictions and clinical circumstances. Four-year PATHFINDER follow-up published in 2026 supports durable activity of avapritinib in advanced disease. Treatment choice requires specialist review of blood counts, bleeding risk, organ function, coexisting haematological disease, interactions and regulatory availability.
Advanced disease and transplantation
SM-AHN requires assessment of both the mastocytosis and the associated neoplasm. Depending on the disease, treatment may include KIT inhibition and therapy directed at the associated myeloid neoplasm. Allogeneic haematopoietic stem-cell transplantation may be considered for carefully selected high-risk patients, but it is not routine treatment for indolent disease.
Important emerging research
Evidence note: some findings in this section are preliminary reports that have not yet undergone full peer review. They may change after complete publication and should inform research and specialist discussion—not independently change treatment.
1. More sensitive and broader molecular diagnosis
The superRCA abstract suggests that very low KIT D816V burdens may be detectable in blood, potentially reducing false-negative results. Another analysis of approximately 5,900 reported adult cases found a higher proportion of non-D816V activating KIT variants in Asian patients than in White cohorts. Although subject to literature and ascertainment bias, this supports mutation-agnostic KIT testing when clinical suspicion remains high after a negative D816V assay.
2. Disease burden, symptoms and quality of life
In the Summit study, improvement in patient-reported symptoms correlated with reductions in serum tryptase, blood KIT D816V variant allele fraction and bone-marrow mast-cell burden. Real-world MASTHAVE app data also suggested different patterns by sex: men reported higher mast-cell burden, osteoporosis and more grade IV reactions, while women reported broader symptoms and greater quality-of-life impairment. These observations need prospective confirmation and should not be used to stereotype individual patients.
3. Bezuclastinib remains investigational
The phase 2 Summit abstract reported greater 24-week symptom improvement with bezuclastinib than placebo in non-advanced systemic mastocytosis, alongside reductions in objective disease measures. The Apex abstract in advanced systemic mastocytosis reported responses and substantial reductions in mast-cell burden markers, with cytopenias among important treatment-related adverse effects. These are encouraging clinical-trial findings, but licensing and routine availability must not be assumed.
4. New registry evidence in SM-AHN
An international registry analysis included 467 patients with myeloid SM-AHN. Prognosis was associated strongly with the aggressiveness of the mastocytosis component. In an observational subgroup with aggressive or leukaemic disease, exposure to midostaurin or avapritinib was associated with longer survival and a lower cumulative incidence of transformation to acute myeloid leukaemia. Because treatment was not randomised, residual confounding is possible.
5. Beyond KIT inhibitors
Preclinical abstracts described mouse models that reproduce aspects of KIT-driven mastocytosis and identified inflammatory pathways that may be relevant to future research. A separate laboratory programme identified the PDE3A–SLFN12 molecular-glue pathway as a potential vulnerability in KIT D816V cells and reported synergy with KIT inhibitors. These findings are laboratory-stage and do not yet constitute a patient treatment.
Mastocytosis in children
Paediatric mastocytosis differs from adult disease. Most children have cutaneous disease, and many improve over time. Bone-marrow biopsy is not performed automatically: the decision depends on organ enlargement, blood-count abnormalities, persistently or markedly raised tryptase, severe systemic symptoms and other concerning features.
A single-centre cohort of 160 children associated repeated baseline tryptase elevation with a history of anaphylaxis, whereas cutaneous mastocytosis alone was not associated with the same level of risk. This requires external validation and does not create a universal numerical threshold for every child, but it supports interpreting serial results alongside the full clinical picture.
A rare paediatric case described aggressive systemic mastocytosis with a non-D816V KIT N822K mutation responding to avapritinib. A single case cannot establish efficacy or safety for children; paediatric advanced disease requires highly specialised multidisciplinary care.
Prognosis and follow-up
Prognosis depends predominantly on subtype. Most patients with indolent systemic mastocytosis have a very low risk of progression and historically have had near-normal life expectancy, although chronic symptoms, anaphylaxis and skeletal disease can be important. Advanced systemic mastocytosis has a different course and requires molecular and clinical risk assessment.
Follow-up may include symptom and anaphylaxis review, blood counts and biochemistry, baseline tryptase, molecular monitoring when informative, bone-health assessment and examination for organ enlargement or dysfunction. The intensity of monitoring should match the subtype and individual risk.
When to seek specialist advice
Assessment may be appropriate for recurrent unexplained flushing or anaphylaxis, severe reactions to bee or wasp stings, persistently raised baseline tryptase, characteristic skin lesions, unexplained osteoporosis or vertebral fractures, unexplained organ enlargement, or a combination of mediator-related and systemic symptoms.
Because mastocytosis can resemble allergic, dermatological, gastrointestinal and haematological conditions, care often involves allergy/immunology, haematology, dermatology, gastroenterology and bone specialists.
References and further reading
Established literature
- Valent P, Akin C, Hartmann K, et al. Updated diagnostic criteria and classification of mast cell disorders: a consensus proposal. HemaSphere. 2021;5:e646. Full text.
- Ustun C, et al. Systemic mastocytosis: current status and challenges in 2024. Blood Advances. 2025;9:2048–2064. Full text.
- Gotlib J, Castells M, Oude Elberink H, et al. Avapritinib versus placebo in indolent systemic mastocytosis. NEJM Evidence. 2023;2:EVIDoa2200339. Article.
- Gotlib J, Reiter A, Radia DH, et al. Efficacy and safety of avapritinib in advanced systemic mastocytosis: interim analysis of the phase 2 PATHFINDER trial. Nature Medicine. 2021;27:2192–2199. PubMed.
- Gotlib J, et al. Efficacy and safety of avapritinib in advanced systemic mastocytosis: 4-year follow-up of the PATHFINDER study. Blood Advances. 2026;10:3676–3689. PubMed.
- Trizuljak J, et al. Clinical features and survival of patients with indolent systemic mastocytosis defined by the updated WHO classification. Allergy. 2020. PubMed.
- Nemat K, et al. Cutaneous mastocytosis in childhood. Allergologie Select. 2022;6:1–10. Full text.
Emerging studies reviewed for this update
Particularly relevant preliminary reports discussed above include:
- Aldegheri F, et al. Long-term skeletal outcomes of zoledronate therapy for mastocytosis-related bone disease.
- Alvarez-Twose I, et al. Mast-cell clonality, HαT and severe food-induced anaphylaxis.
- Bodbin S, et al. Ultra-sensitive superRCA testing for KIT D816V.
- Gourguechon C, et al. Real-world avapritinib outcomes in indolent systemic mastocytosis.
- Panse J, Siebenhaar F, George TI, Boggs NA, et al. Summit trial analyses of bezuclastinib in non-advanced systemic mastocytosis.
- Radia DH, et al. Apex study of bezuclastinib in advanced systemic mastocytosis.
- Rossignol J, et al. International registry outcomes in systemic mastocytosis with an associated myeloid neoplasm.
- Rama TA, et al. Dietary histamine and symptom severity in mastocytosis.
- Mol N, et al. Repeated basal tryptase elevation and anaphylaxis in children.
- Zenke M, et al. PDE3A–SLFN12 molecular glues as a preclinical non-TKI strategy.
Medical disclaimer
This article is for general education and does not replace individual medical assessment, diagnosis or treatment. Findings described as emerging or preliminary should not be used to start, stop or change treatment without advice from an appropriately qualified specialist. Medicine licensing and availability vary by country and can change.